Precision Medicine Approaches in Oncology: From Tumour Profiling to Treatment Decisions

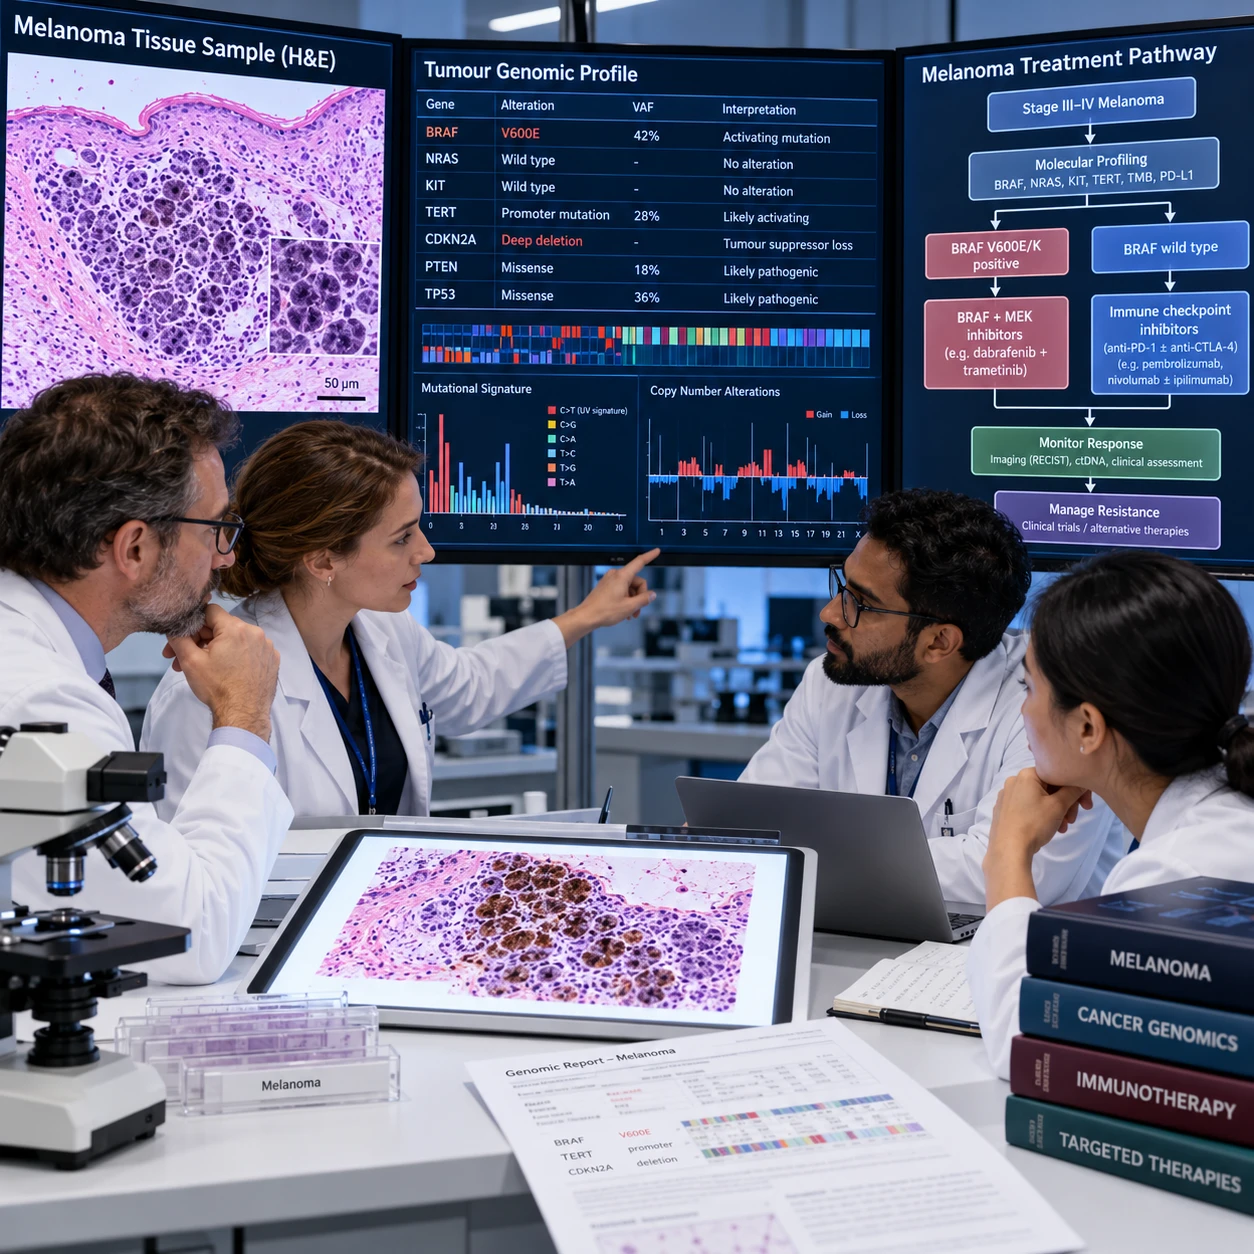
Precision medicine approaches in oncology use information about a cancer’s biology, as well as a patient’s health and circumstances, to help guide care. Tumour profiling can identify features that may make some treatments more relevant, but no test can guarantee a response or select the right option on its own.
These approaches bring together laboratory testing, clinical evidence and specialist judgment. They are used across cancer types, including melanoma, where certain tumour biomarkers can inform decisions about targeted therapy, immunotherapy or clinical trial eligibility.
What precision medicine means in oncology
Precision medicine in oncology uses measurable features of a tumour and other patient information to help tailor cancer care. It adds biological detail to decisions that have traditionally relied heavily on cancer type, location, stage and the person’s overall health.
For example, two cancers arising in the same organ may have different molecular changes. Those differences can affect how the cancers behave and whether a particular treatment is biologically relevant. Conversely, a molecular feature found in cancers from different organs may sometimes point to the same treatment or trial, depending on the evidence and the treatment’s approval.
Precision oncology is not a separate treatment in itself. It is a way to gather and interpret evidence before choosing among available options. A treatment decision may also consider the cancer’s stage, previous therapies, expected benefits and risks, the patient’s preferences, and whether a suitable clinical trial is available.
The term can describe a range of approaches, from testing for one well-established biomarker to broader genomic testing. It does not mean every patient will have an actionable finding, or that a molecular match is automatically better than standard care.
How tumour characteristics inform care
Tumour profiling examines cancer cells for features that may affect prognosis or treatment choice. Results from genomic testing and other assessments are interpreted alongside the clinical picture to determine whether a finding is relevant.
Testing may examine DNA changes, such as mutations or gene fusions, or assess proteins and other markers in tumour tissue. Depending on the question, a laboratory may test a single biomarker or use a panel that evaluates many genes at once. Some tests can also analyse a blood sample for tumour-derived DNA, though a blood-based result may not capture every feature present in the cancer.
Biomarkers can serve different purposes. Some help identify a treatment target; others may provide information about likely response, disease behaviour or eligibility for research. A result’s meaning depends on the specific cancer, the test’s accuracy, the evidence supporting its use and the treatment being considered.
- Tissue biopsy: A sample of tumour is examined in a laboratory. It can provide detailed information, but may reflect only the sampled area and time point.
- Genomic testing: DNA or RNA analysis can detect selected molecular alterations. A broader panel may reveal more findings, but can also produce results with uncertain significance.
- Protein or immune markers: Tests can assess features that relate to tumour biology or immune activity, depending on the clinical question.
- Clinical context: Imaging, pathology, prior treatment and the person’s health help determine whether a laboratory finding can guide a practical decision.
When a result is unclear, a multidisciplinary team may include oncologists, pathologists, molecular biologists and genetic specialists. The team can distinguish an established treatment biomarker from a finding that remains exploratory.
Targeted therapies and immunotherapy
Targeted therapy acts on particular molecules or pathways that contribute to cancer growth, while immunotherapy helps the immune system recognise or attack cancer. Biomarker results can inform whether either approach is worth considering, but the evidence and expected benefit vary.
A targeted drug may be relevant when a tumour carries a specific alteration that the medicine is designed to address. In some cancers, testing for that alteration is important before treatment. Yet the presence of a target does not ensure that the cancer will respond: other molecular changes, resistance mechanisms and the surrounding tumour environment can influence the outcome.
Immunotherapy, including immune checkpoint inhibitors, works differently. It aims to restore or strengthen immune activity against cancer. Certain tumour or immune features may help inform treatment decisions in particular settings, but they are not universal predictors. A biomarker can be associated with a greater chance of benefit without identifying every patient who will respond or excluding everyone who might.
These approaches may be considered separately or in a sequence, depending on cancer type, stage, prior treatment, clinical evidence and the patient’s situation. Choosing one option can mean accepting trade-offs, such as different side-effect profiles, treatment schedules or uncertainty about how long benefit may last. A care team weighs these factors rather than treating a test result as a prescription.
Precision medicine in melanoma
Precision medicine is part of melanoma research and care, particularly when tumour testing identifies a molecular feature that can inform targeted treatment or trial options. The result must still be interpreted in the context of melanoma subtype, disease stage and the available evidence.
For some melanomas, testing for alterations in genes such as BRAF can help clinicians assess whether a BRAF- and MEK-targeted treatment is relevant. The test does not determine every aspect of care, and it does not guarantee that treatment will work. Immunotherapy is also an important treatment approach in melanoma; its use is guided by clinical factors and evidence, not simply by the assumption that every tumour has a single decisive biomarker.
Melanoma highlights a central challenge in precision oncology: cancers can differ between patients and within the same patient. A biopsy from one tumour site may not fully represent another site, and a tumour’s biology can change after treatment. Researchers therefore study how genomic results, pathology, immune features and treatment history can be combined to make more useful decisions.
For patients and clinicians, the practical question is not merely, “Was a biomarker found?” It is whether the finding is reliable, clinically meaningful for this melanoma, and linked to an option with evidence of benefit in this situation. Specialist interpretation matters, especially when results are complex or treatment choices are close.
Challenges and limitations
Precision medicine has important limits: tumours evolve, tests sample only part of a cancer, and a biomarker does not guarantee treatment response. Access to testing and suitable therapies also varies across health systems and clinical settings.
Tumour heterogeneity means that cancer cells may not all share the same features. A biopsy captures a snapshot from one location, so another tumour area or metastasis may carry different alterations. Treatment can also apply pressure that favours resistant cells, changing the tumour over time. A result obtained before treatment may therefore become less informative later.
Test interpretation presents another challenge. A broad genomic panel may identify a change whose significance is uncertain, or a biomarker supported in one cancer type may not have the same meaning in another. Testing can also fail to produce a usable result if there is too little tissue or the sample quality is poor.
- Assuming every finding is actionable: A molecular alteration may have no proven treatment match. Ask whether the evidence supports routine care, a trial, or further study.
- Treating a negative result as a complete picture: A test checks for specified features in a particular sample. It cannot rule out every possible biomarker or account for all tumour differences.
- Equating a match with a guaranteed response: A drug may target a relevant pathway, but resistance and other biological factors can limit benefit. Discuss likely outcomes and alternatives with the oncology team.
Access can depend on local testing capacity, cost, tissue availability and whether a matched medicine or trial is open. Precision medicine is most useful when the test is chosen for a clear clinical question and its result is considered alongside other evidence.
The role of research and clinical trials
Clinical trials test whether precision approaches improve outcomes and help define which patients are most likely to benefit. They can evaluate new drugs, biomarker-guided treatment strategies, combinations and ways to monitor changing tumours.
Trials may recruit participants based on a particular alteration, a cancer type, prior treatment or another feature. Some studies compare a biomarker-guided approach with standard care; others examine a new therapy when established options have limited benefit. Eligibility criteria are specific, so finding a biomarker does not automatically mean a person qualifies.
Research also asks how best to handle tumour heterogeneity and resistance. Studies may compare tissue biopsy with blood-based testing, examine samples collected at different times, or combine genomic information with pathology and immune data. These efforts can clarify when retesting is useful and which findings should change care.
For melanoma and other cancers, well-designed trials are essential because promising biological reasoning is not the same as demonstrated clinical benefit. Patients considering a study can discuss its purpose, procedures, possible risks, alternatives and practical demands with their care team. Trial participation is voluntary, and standard treatment options should be explained clearly alongside research opportunities.
Frequently asked questions
What is precision medicine in oncology?
Precision medicine in oncology uses tumour biomarkers, genomic testing and clinical information to help guide cancer care. It can identify treatment options or trials to consider, but does not guarantee a particular treatment will work.
How does tumour profiling help guide treatment?
Tumour profiling looks for molecular, genetic or protein features that may be linked to a treatment or provide other clinically useful information. An oncology team interprets the result in light of the cancer type, stage, evidence and patient’s health.
Is precision medicine used for melanoma?
Yes. Biomarker testing can inform treatment decisions for some melanomas, including consideration of targeted therapy when a relevant alteration is present. Immunotherapy and other care decisions also depend on the clinical situation, not on one test alone.
Does finding a biomarker mean a treatment will work?
No. A biomarker may make a treatment biologically relevant, but it cannot predict response with certainty. Tumour heterogeneity, resistance and other clinical factors can affect whether a treatment helps.